
Healthcare AI Agent Implementation: Architecture, HIPAA and Human Oversight is designed for teams moving from AI experimentation to a governed business capability. The useful question is not whether a model can produce an impressive answer. It is whether a system can complete a defined job, use approved data and tools, stop at the right boundary, recover from failure, and leave evidence that people can audit.
This guide takes a compliance-aware implementation guide that supports DreamzTech’s existing healthcare industry page instead of targeting the same head term. It separates proven engineering patterns from marketing shorthand and gives buyers, product leaders and technical teams a shared way to make decisions.
Quick answer: A reliable healthcare AI agent implementation initiative starts with one bounded workflow, explicit success and failure criteria, narrow permissions, representative evaluation cases, human control over consequential actions, and a measured rollout. Model selection matters, but the surrounding software and operating controls usually determine whether the agent survives production.
What readers should take away
- How to evaluate healthcare AI agent implementation without confusing a prototype with a production system
- Which architecture and operating controls matter most
- How to define a safe first release and measurable acceptance criteria
- Where DreamzTech services, solutions and implementation evidence can support the next step
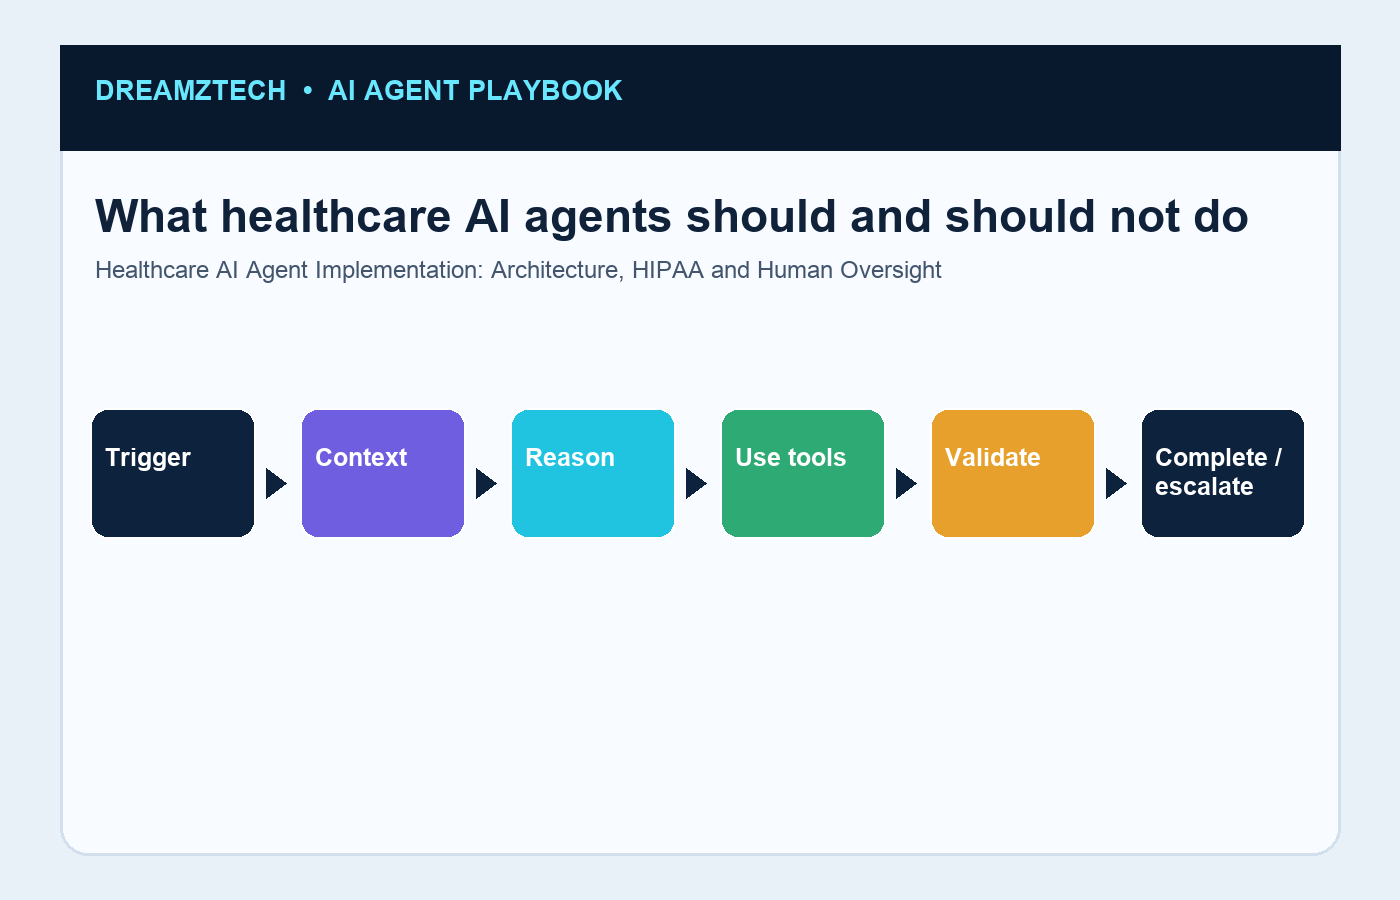
What healthcare AI agents should and should not do
Start by naming the actor, trigger, inputs, systems of record, permitted actions and completion condition. If the team cannot draw the workflow and identify its owner, an agent will inherit that ambiguity. The first design artefact should therefore be an operational boundary, not a prompt.
In healthcare, distinguish administrative automation and clinical decision support. Privacy, safety, applicable law, organizational policy and qualified human oversight must shape the workflow before any access to protected health information is granted.
- Define a named owner and measurable completion condition
- Limit tools and data to the minimum required
- Add explicit exception, escalation and recovery paths
- Test with representative and adversarial scenarios
Administrative and clinical-support use cases
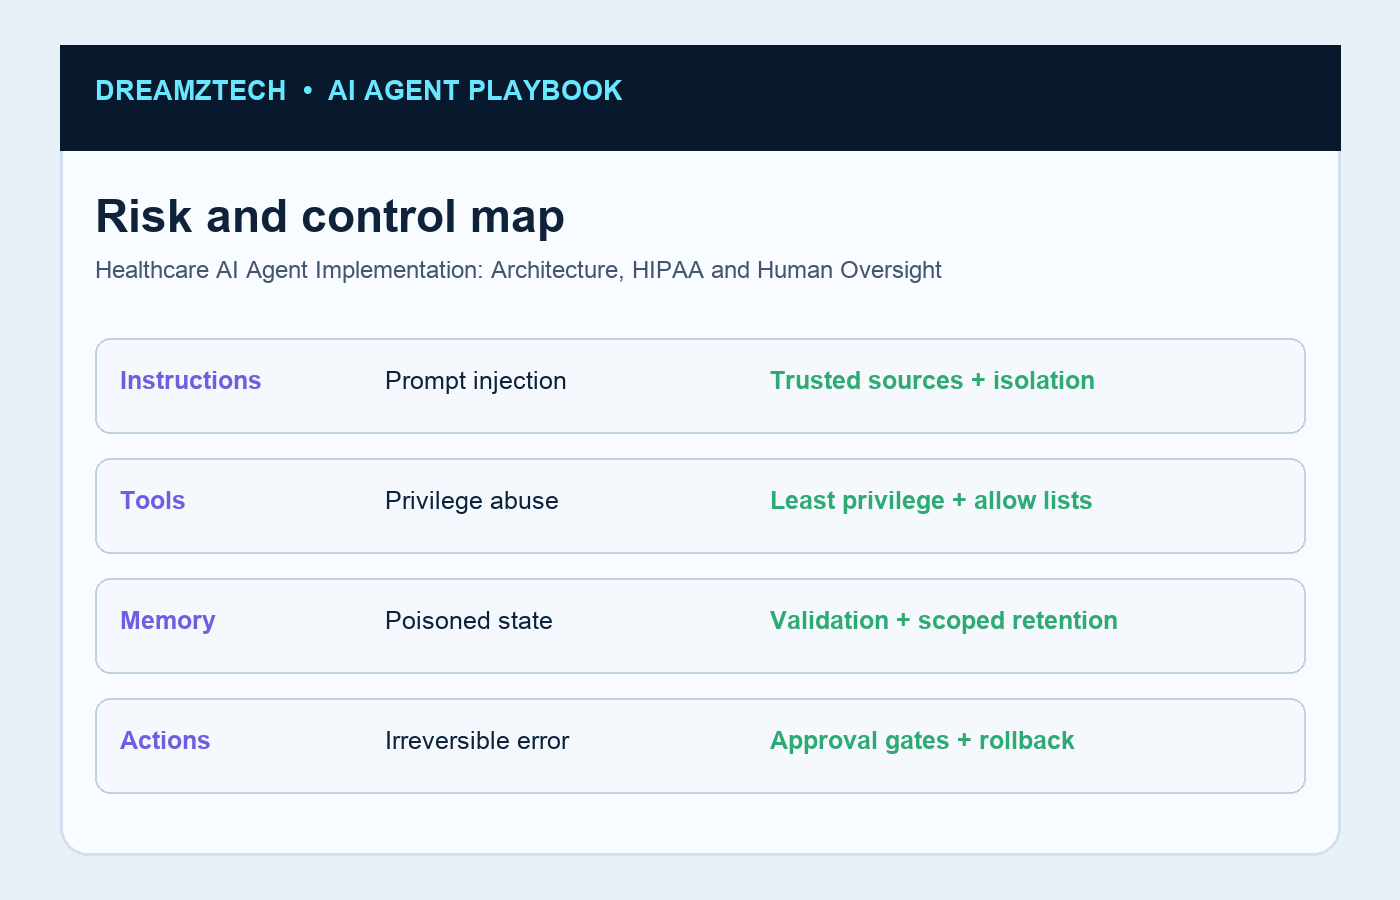
Separate deterministic business rules from model judgement. Validation, permissions, monetary limits, routing rules and irreversible actions belong in explicit software controls. The model can interpret messy input and select among allowed tools, but it should not invent its own authority.
In healthcare, distinguish administrative automation and clinical decision support. Privacy, safety, applicable law, organizational policy and qualified human oversight must shape the workflow before any access to protected health information is granted.
- Define a named owner and measurable completion condition
- Limit tools and data to the minimum required
- Add explicit exception, escalation and recovery paths
- Test with representative and adversarial scenarios

Reference architecture and data flows
Treat every tool as a contract. Define accepted inputs, returned outputs, timeouts, idempotency behaviour, error classes and the credentials required. Narrow tools make an agent easier to test, easier to revoke and much easier to explain during a security review.
In healthcare, distinguish administrative automation and clinical decision support. Privacy, safety, applicable law, organizational policy and qualified human oversight must shape the workflow before any access to protected health information is granted.
- Define a named owner and measurable completion condition
- Limit tools and data to the minimum required
- Add explicit exception, escalation and recovery paths
- Test with representative and adversarial scenarios
HIPAA, privacy and vendor responsibilities
Ground the agent in the minimum context needed for the task. Retrieval should respect the requesting user's entitlements, cite the underlying record where practical, and abstain when evidence is incomplete. More context is not automatically better context.
In healthcare, distinguish administrative automation and clinical decision support. Privacy, safety, applicable law, organizational policy and qualified human oversight must shape the workflow before any access to protected health information is granted.
- Define a named owner and measurable completion condition
- Limit tools and data to the minimum required
- Add explicit exception, escalation and recovery paths
- Test with representative and adversarial scenarios
Identity, access and audit controls
Evaluate complete trajectories rather than final prose. A successful run uses the right data, chooses the right tool, handles partial failure, requests approval when required and stops when the job is complete. Scenario suites should include normal cases, edge cases, malicious inputs and dependency outages.
In healthcare, distinguish administrative automation and clinical decision support. Privacy, safety, applicable law, organizational policy and qualified human oversight must shape the workflow before any access to protected health information is granted.
- Define a named owner and measurable completion condition
- Limit tools and data to the minimum required
- Add explicit exception, escalation and recovery paths
- Test with representative and adversarial scenarios
Human review and clinical safety
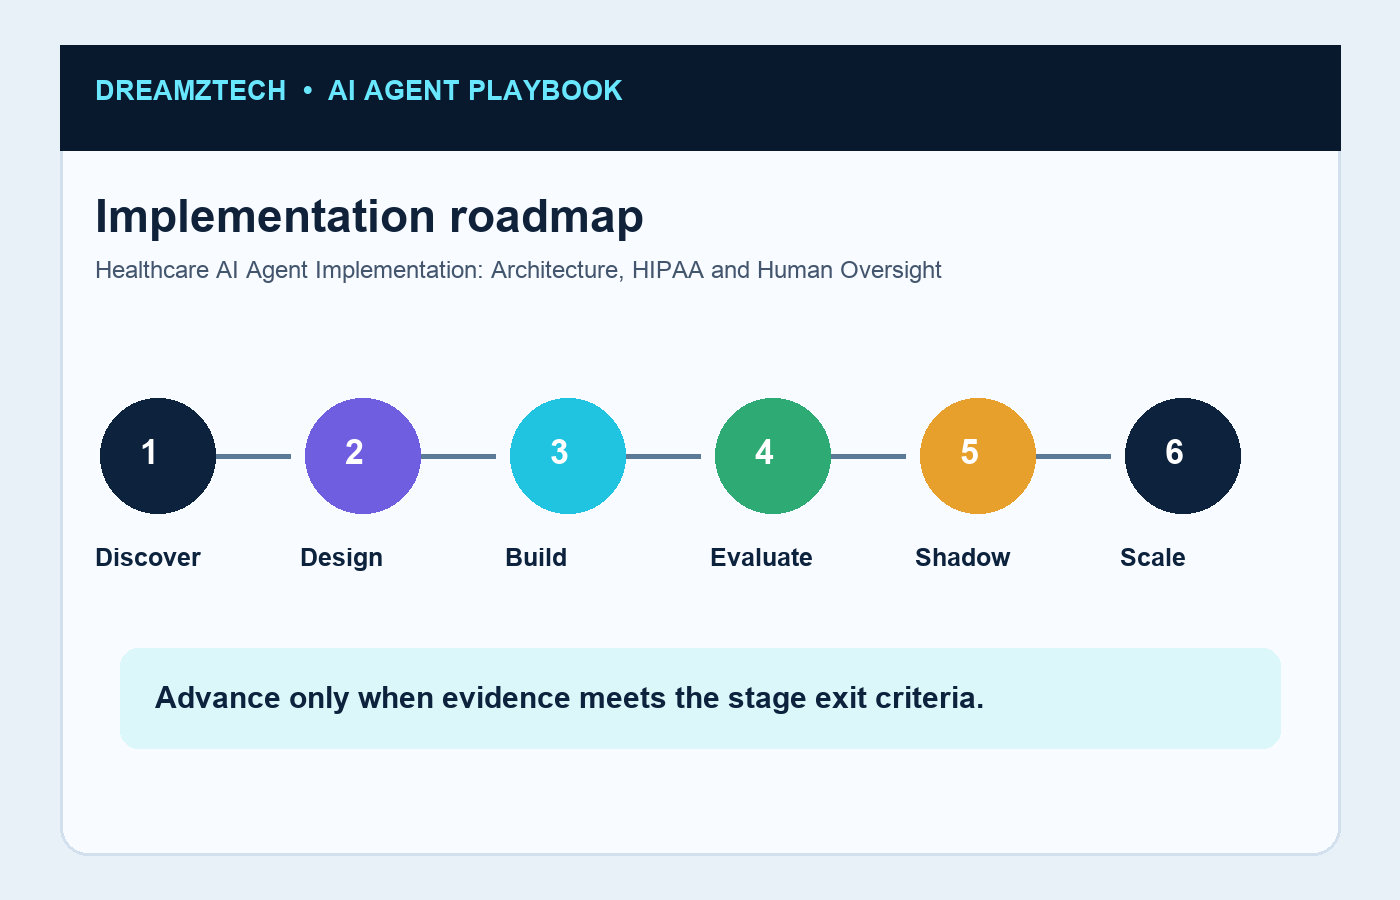
Release in stages: offline evaluation, a sandbox connected to test systems, shadow mode in which the agent proposes without acting, a narrow live slice, and only then broader authority. Each stage needs an owner, exit criteria, a tested disable path and a rollback plan.
In healthcare, distinguish administrative automation and clinical decision support. Privacy, safety, applicable law, organizational policy and qualified human oversight must shape the workflow before any access to protected health information is granted.
- Define a named owner and measurable completion condition
- Limit tools and data to the minimum required
- Add explicit exception, escalation and recovery paths
- Test with representative and adversarial scenarios
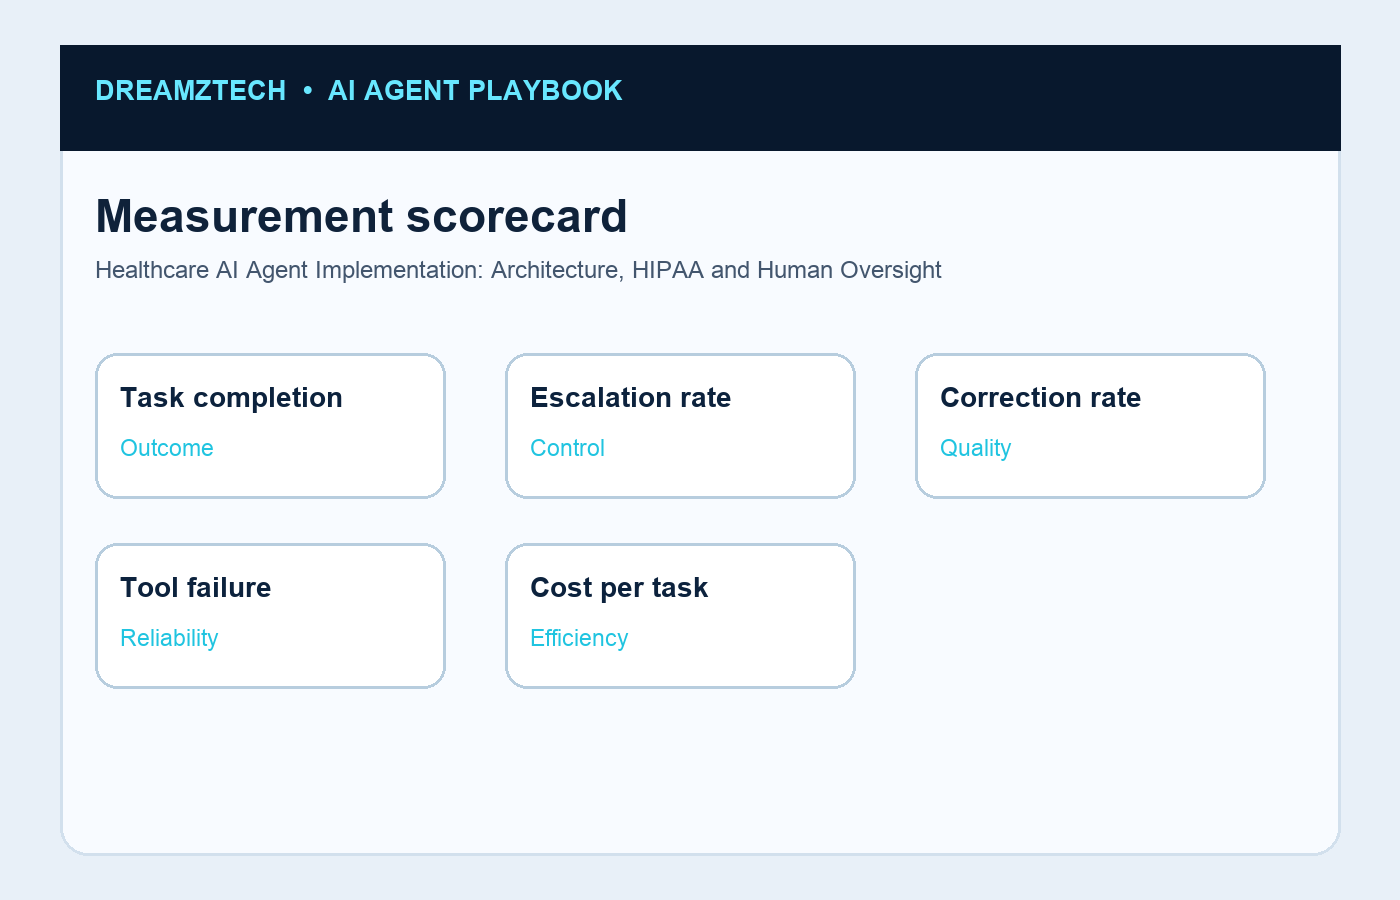
Evaluation with representative data
Measure task outcomes, not token activity. Useful metrics include completion rate, escalation rate, correction rate, tool-call failure rate, latency, cost per completed task, policy violations and business impact. Review the failures behind the averages because they reveal where controls or workflow design need attention.
In healthcare, distinguish administrative automation and clinical decision support. Privacy, safety, applicable law, organizational policy and qualified human oversight must shape the workflow before any access to protected health information is granted.
- Define a named owner and measurable completion condition
- Limit tools and data to the minimum required
- Add explicit exception, escalation and recovery paths
- Test with representative and adversarial scenarios
Implementation roadmap
Ownership continues after launch. Business operations owns the outcome and policy; engineering owns reliability and integration; security owns control requirements; and a named product owner decides what changes. Models, prompts, APIs and source data drift, so evaluation and review must be continuous.
In healthcare, distinguish administrative automation and clinical decision support. Privacy, safety, applicable law, organizational policy and qualified human oversight must shape the workflow before any access to protected health information is granted.
- Define a named owner and measurable completion condition
- Limit tools and data to the minimum required
- Add explicit exception, escalation and recovery paths
- Test with representative and adversarial scenarios
Recommended next step
Use this guide to create a one-page scope, then compare it with DreamzTech’s AI agents for healthcare, healthcare AI agent development, secure AI implementation. The purpose of these links is to move a reader from education to the most relevant service or proof page without making this article compete with the commercial landing page.
Turn one workflow into a production plan
Begin with a low-risk administrative workflow and explicit privacy, safety and human-review controls.
Frequently asked questions
What are AI agents in healthcare?
A useful answer depends on workflow scope, action authority, data sensitivity, integrations and acceptance criteria. Start with a bounded task, narrow permissions, representative tests and a clear human escalation path; expand only when evidence supports it.
Can an AI agent be HIPAA compliant?
A useful answer depends on workflow scope, action authority, data sensitivity, integrations and acceptance criteria. Start with a bounded task, narrow permissions, representative tests and a clear human escalation path; expand only when evidence supports it.
Should AI agents make clinical decisions?
A useful answer depends on workflow scope, action authority, data sensitivity, integrations and acceptance criteria. Start with a bounded task, narrow permissions, representative tests and a clear human escalation path; expand only when evidence supports it.
How should PHI access be controlled?
A useful answer depends on workflow scope, action authority, data sensitivity, integrations and acceptance criteria. Start with a bounded task, narrow permissions, representative tests and a clear human escalation path; expand only when evidence supports it.
What is a safe first healthcare use case?
A useful answer depends on workflow scope, action authority, data sensitivity, integrations and acceptance criteria. Start with a bounded task, narrow permissions, representative tests and a clear human escalation path; expand only when evidence supports it.
Standards and primary references
Editorial note: This article provides general technology and implementation guidance, not legal, medical or compliance advice. Requirements should be validated for the organization, jurisdiction and use case.


